The Endocrine System
The Endocrine System
The endocrine system uses chemical messengers called hormones to coordinate and control body functions (B3.2a). Unlike the nervous system, which produces fast, short-lived, precise responses via electrical impulses, the endocrine system produces slower, longer-lasting and more widespread responses.
Hormones are produced by endocrine glands and released directly into the blood, which transports them to their target organs. Each hormone has specific target cells with receptors that recognise it — only cells with the correct receptor will respond to a particular hormone. Key endocrine glands include the pituitary gland (often called the "master gland" because it controls other glands), the thyroid gland, the adrenal glands, the pancreas and the ovaries/testes.
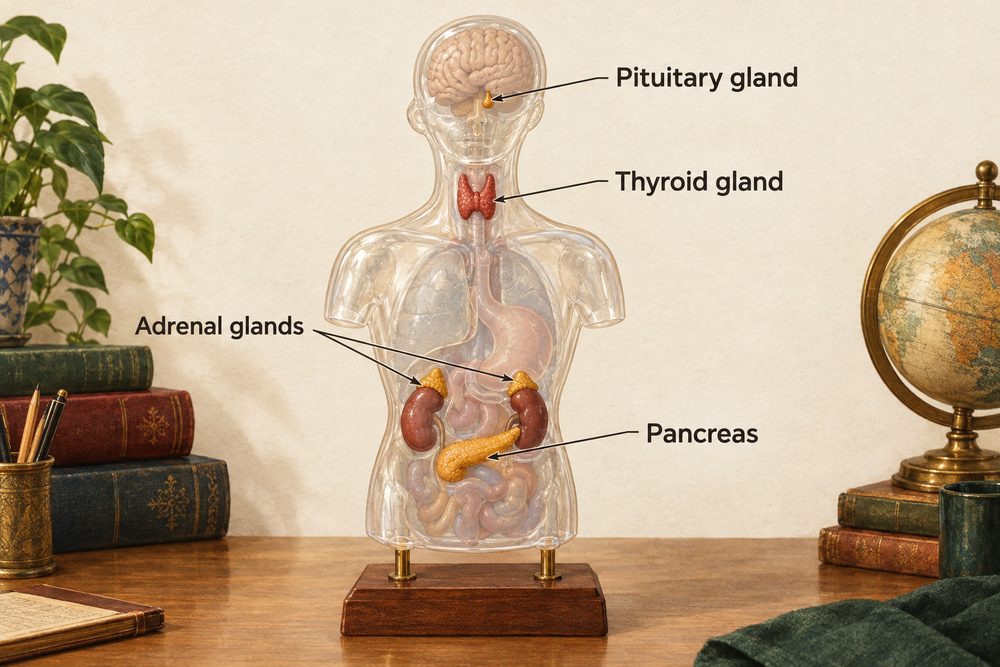
The endocrine system uses hormones (chemical messengers) transported in the blood to target organs with specific receptors. Responses are slower but longer-lasting than the nervous system. The pituitary gland is the "master gland" that controls other endocrine glands.
Thyroxine is produced by the thyroid gland and controls metabolic rate — the speed of chemical reactions in cells. It is regulated by negative feedback (B3.2b, Higher Tier): when thyroxine levels are high, the pituitary gland reduces production of TSH (thyroid-stimulating hormone), which in turn causes the thyroid to produce less thyroxine. When thyroxine levels drop too low, the pituitary increases TSH, stimulating more thyroxine production. This feedback loop keeps thyroxine levels stable.
Adrenaline is produced by the adrenal glands (located on top of the kidneys) in response to stress, danger or excitement (B3.2b). It triggers the "fight or flight" response: heart rate increases, breathing rate increases, blood is diverted from the gut to the muscles, glycogen in the liver is converted to glucose for extra energy, and the pupils dilate. These changes prepare the body to respond quickly to a threat.
Hormones in Human Reproduction
The menstrual cycle is a roughly 28-day cycle controlled by four key hormones interacting through feedback mechanisms (B3.2c–d). Testosterone, produced by the testes, controls the development of male secondary sexual characteristics and sperm production.
The four hormones controlling the menstrual cycle are:
FSH (follicle-stimulating hormone) — produced by the pituitary gland, stimulates the maturation of an egg in the ovary (inside a follicle). Oestrogen — produced by the ovaries, repairs and thickens the uterus lining after menstruation, inhibits further FSH production, and stimulates the release of LH. LH (luteinising hormone) — produced by the pituitary gland, a surge of LH triggers ovulation (release of the mature egg from the ovary, around day 14). Progesterone — produced by the empty follicle (now called the corpus luteum), maintains the thick uterus lining ready for implantation. If no fertilisation occurs, progesterone levels drop, the lining breaks down, and menstruation begins.
The menstrual cycle is controlled by FSH (matures egg), oestrogen (repairs lining, triggers LH), LH (triggers ovulation) and progesterone (maintains lining). These hormones interact in feedback loops over a ~28-day cycle.
Hormonal contraception (B3.2e) includes the combined pill (contains oestrogen and progesterone), the mini-pill (progesterone only), implants and injections. These work by maintaining high levels of oestrogen and/or progesterone, which inhibit FSH production from the pituitary. Without FSH, no egg matures, so ovulation does not occur. Hormonal methods are highly effective (over 99%) but can cause side effects such as headaches, mood changes and blood clots (rare).
Non-hormonal methods include: condoms (barrier method — prevent sperm reaching the egg and also protect against sexually transmitted infections), diaphragms (barrier placed over the cervix), copper IUDs (intrauterine devices that create an environment hostile to sperm), and surgical sterilisation (permanent). Non-hormonal methods do not affect the hormonal cycle but vary in effectiveness.
The OCR spec expects you to evaluate both types — consider effectiveness, side effects, convenience, protection against STIs, and whether the method is reversible.
Fertility treatments use hormones to help people who have difficulty conceiving (B3.2f, Higher Tier). FSH and LH injections can stimulate ovulation in women whose pituitary gland does not produce enough of these hormones naturally. This is called ovulation induction.
IVF (in vitro fertilisation) involves giving FSH to stimulate the ovaries to produce multiple eggs, collecting the eggs surgically, fertilising them with sperm in a laboratory dish, allowing the embryos to develop for a few days, and then implanting one or two embryos into the uterus. IVF success rates are around 25–30% per cycle. It is expensive, physically and emotionally demanding, and raises ethical concerns about unused embryos. However, it has allowed millions of people to have children who otherwise could not.
Plants also use hormones to coordinate growth and development. Auxin is a key plant hormone produced in the tips of shoots and roots. It controls phototropism (growth towards light) and gravitropism (growth in response to gravity).
In phototropism, light causes auxin to move to the shaded side of the shoot. Higher auxin concentration on the shaded side causes cells there to elongate more, bending the shoot towards the light. In gravitropism, auxin accumulates on the lower side of a horizontal root, where it inhibits cell elongation (the opposite effect to shoots), causing the root to grow downwards. In agriculture, synthetic auxins are used as selective weedkillers and rooting powders.